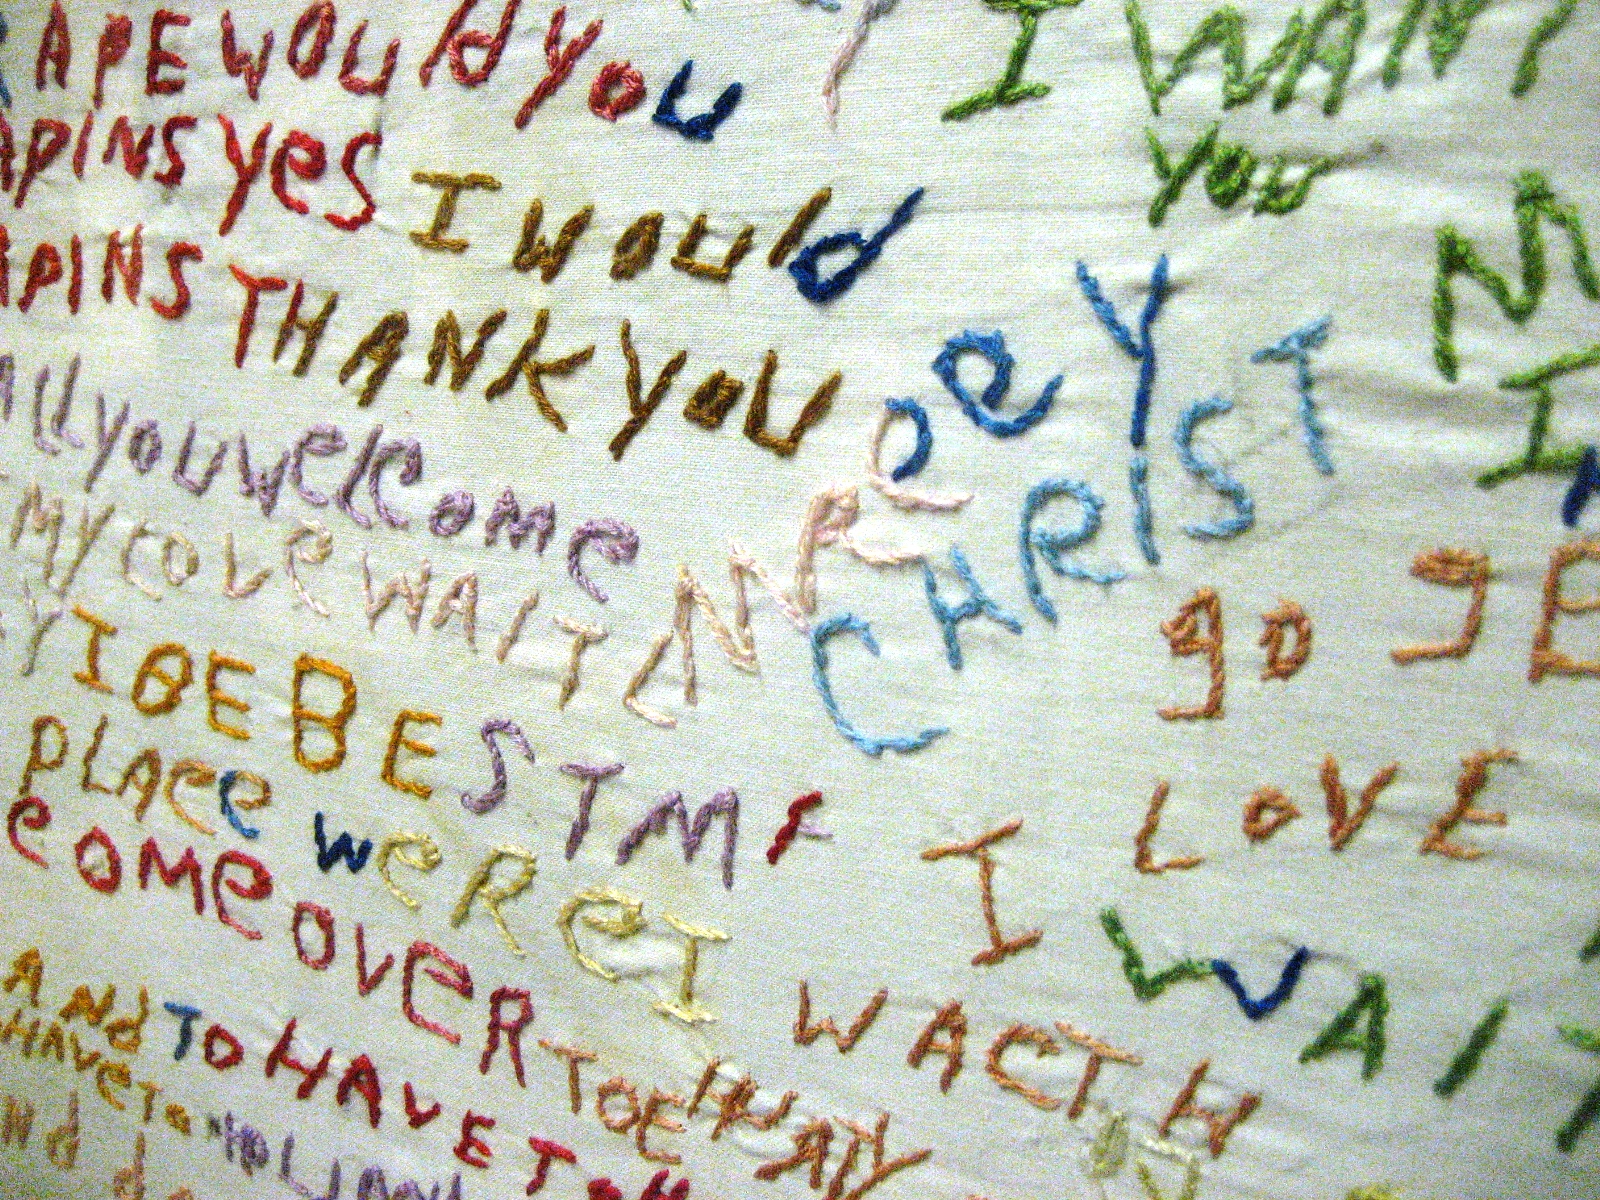Pages

Showing posts with label clinical research. Show all posts

Tuesday, October 2, 2018

How to be Opportunistic, Not Manipulative


By Nathan Ahlgrim


Opportunistic Research


Government data is often used to

answer key research questions.

Image courtesy of the U.S. Census Bureau


Opportunistic research has a long and prosperous history across the sciences. Research is classified as

opportunistic when researchers take advantage of a special situation. Quasi-experiments enabled by government programs, unique or isolated populations, and once-in-a-lifetime events can all trigger opportunistic research where no experiments were initially planned. Opportunistic research is not categorically problematic. If anything, it is categorically efficient. Many a study could not be ethically, financially, or logistically performed in the context of a randomized control trial.


Biomedical research is certainly not the only field that utilizes opportunistic research, but it does present additional ethical challenges. In contrast, many questions in social science research can only be ethically tested via opportunistic research, since funding agencies are wary of explicitly withholding resources from a ‘control’ population (Resch et al., 2014). We, as scientists, are indebted to patients who choose to donate their time and bodies to participate in scientific research while inside an inpatient ward; their volunteerism is the only way to perform some types of research.


Almost all information we have about human neurons comes from generous patients. For example, patients with treatment-resistant epilepsy can have tiny wires lowered into their brains, a technique known as intracranial microelectrode recording, enabling physicians to listen in on the neuronal chatter at a resolution normally restricted to animal models (Inman et al., 2017; Chiong et al., 2018). Seizures, caused by runaway excitation of the brain, are best detected by recording electrical signals throughout the brain. By having such fine spatial resolution inside a patient’s brain, surgeons can be incredibly precise in locating the site of the seizure and treating the patient. It’s what else those wires are used for that introduces thorny research ethics.


Image courtesy of Wikimedia Commons.

Those wires are already down there, so why not put them to even more use? Scientists dream of poring over the treasure trove of patients’ data. It’s a precious, and rare, resource. The elephant in the room, especially for practitioners of basic research, is that basic research is not expected to directly benefit the individual patient. Any scientific gain may help people in the years to come, but it will not affect that individual patient’s prognosis. Unlike studies trying to optimize deep brain stimulation (DBS) for treatment of Parkinson’s Disease (Müller and Christen, 2011) or depression (Dunn et al., 2011), basic research exists for the sake of science, not patient welfare. With fewer concrete benefits to the patient, the risk to benefit calculation becomes trickier.


Human neuroscience research like this is almost always expensive and demanding. That does not mean, however, that these experiments can be low priority. Our prodigious knowledge of the nervous system is only surpassed by our ignorance of it, and treatments for some of the most pressing health concerns of our time depend on research like this increasing our knowledge. Of course, such a strong motivation to innovate can blind scientists to the need to also protect their research participants, which is why specific ethical standards for opportunistic research need to be robust and ready.


Physician-led Opportunism


In the physician-patient relationship, the power dynamic lies in favor of the physician. Most physicians recognize and accept this dynamic when it comes to healthcare. Even so, many fail to appreciate that the power dynamic does not disappear when the conversation changes topic; the physician remains the physician even when she talks to her patient about non-therapeutic research.


Image courtesy of SVG Silh.


Non-medical invasive brain research, like that using intracranial recordings and brain stimulation in epilepsy patients, is admittedly a niche area. Since it has no immediate
implications for human health, it receives far less publicity and
public scrutiny than clinical trials or even promising treatments in
animal models (Fang and Casadevall, 2010). Although the purpose of basic
research is distinct, it can still benefit from the lessons learned on
the medical side. Clinical human neuroscience research shows that the ability to consent does not guarantee that the decision to consent is a voluntarily one (Swift, 2011). In the shadow of the physician-patient power dynamic, would-be participants can become situationally incapacitated even while retaining full mental capacity (Labuzetta et al., 2011). In effect, their position as a patient, the physician-patient relationship, and the overlap between medical and research practices can all render the patient incapable of freely giving informed consent. Although the mental state of the patient may be sound, many argue that they must be protected just like those who lack the mental capacity to consent on their own behalf. The fear is that any hint of the research influencing the medical care, or even the absence of addressing that interaction explicitly, can force the patient’s decision.


Of course, there is also a strong argument that consent, even if not fully voluntary, can be ethically valid. Even proponents of the so-called Autonomous Authorization criterion, under which consent is only valid when given intentionally, with full understanding, and without controlling influence (Faden and Beauchamp, 1986), often amend or bend those strict guidelines to make them practical (Miller and Wertheimer, 2011). Autonomous authorization can be eroded because of therapeutic misconception of research, when potential participants are influenced to enroll in a study due to confusion between research and medical treatment (Appelbaum et al., 1982). For instance, patients may enroll in a study testing a potential drug to treat Alzheimer’s Disease because they believe they will not be placed in the placebo group given their advanced condition. That is not how randomized control trials are designed. Patients’ misunderstanding inflates the benefits in their mind, which could sway their decision to participate. Yet the demand that all patients be fully knowledgeable before their consent is deemed valid may be too rigorous to be practical, and end up an unrealistic burden to place on researchers. Critics of the Autonomous Authorization model claim that responsibility for protecting patients resides in institutional safeguards (i.e. Institutional Review Boards [IRBs]), not the researchers themselves. With strong institutional standards in place, patients’ best interests can still be protected even if they give non-autonomous consent. That is, at least, the argument. How those safeguards are designed is the determining factor of their effectiveness.


How to Keep Consent Voluntary


We cannot pretend that the physician-patient power dynamic does not exist, or that every patient will become an expert in the research program they sign up for. Still, proactive steps on the institutional and personnel sides can protect participants and make sure they enroll because they want to, not because they feel they have to. The need for such protections is compounded by the specifics to invasive brain research, whose entire participant pool lives with a treatment-resistant brain disorder severe enough to merit invasive brain surgery. It is our unfortunate reality that stigma looms over people living with brain disorders, both external (from others) and internal (self-perception) (Corrigan et al., 2006). Stigma surrounding brain disorders weakens personal empowerment (Corrigan, 2002), tipping the balance of power even more strongly towards the physician and research team. The protections put in place for these participants must be comprehensive and robust to rebalance the relationship.


Teams performing invasive brain research have already made a series of recommendations to directly address the unique environment of non-medical invasive research using human patients (Chiong et al., 2018). Their recommendations are strong and worth implementing, but they fall short because of a common blind spot: they are still thinking like researchers, not patients.


Image courtesy of Pixabay user Catkin.

As a patient, you might be coerced to consent to any research protocol put in front of you out of fear that your medical treatment is dependent on it. You don’t even need to be a cynic who expects the worst out of your physician to fear this. After all, your physician will probably take more of an interest in you, and you’ll get more face time with her, if you sign up for her study. Yes, preferential treatment is wrong, but self-defense against improper treatment requires self-empowerment, something that is often degraded in these patients by the stigma following their brain disorder. To minimize potential coercion, physicians should at the very least complete the consent process as part of a team, alongside people not involved in the patient’s care. Of course, the coercion patients feel would be minimized if their physicians were completely absent during the consent process to minimize any implicit coercion, but such requirements are often impractical. Both medical and research personnel should also be required to explicitly state that medical care will not change for the better or worse regardless of research participation. These statements must be unequivocal, and repeated before, during, and after the consent process.


Even as I and others lay out a list of criteria for researchers to meet, it is important to stress that research teams cannot rely on a one-size-fits-all consent process. Individualization is especially necessary when researchers are working with a vulnerable population dependent on their care. The capacity to consent to medical interventions (which get the patient into the ward in the first place) does not imply the capacity to consent to research interventions. Even after patients do consent, their medical condition can fluctuate, as can their desire to participate. Just like with medical treatment, consent at the start of a project (no matter how ethically it was obtained) cannot be used to rubberstamp the entire study. Such protections are already given to psychiatric patients (Palmer et al., 2013), showing that the best consent is one that is renewed.


Institutional criteria can help bolster these practices, but relying too much on them is dangerous. After all, institutional priorities can bias the definition of “patient interests” and preferentially validate non-autonomous consent that aligns with institutional interests over the individual patient’s interest. Both personnel and institutional approaches fail to fully protect the patient/research participant dual role, which is why the two must work in tandem. It is far too easy for researchers to capitalize on a patient’s therapeutic misconception because it produces the desired outcome, even when the deception is unintentional.


Image courtesy of Wikipedia.

As a patient, being told your medical care is protected regardless of your research participation is not the same as believing it and trusting it to be true. Doubt may be unavoidable, and it is not preferable, but it should also not prevent the study from happening. Invasive brain research can only happen in specific and intensive situations, but it is absolutely necessary to the progress of neuroscience and medicine. Everything from epilepsy to Alzheimer’s Disease to autism is informed by and better treated because of invasive brain research.


Patients will be protected when physicians are trained to not display favoritism to their research participants and IRBs shape research protocols to fairly balance a participant’s risks and benefits. They will be protected even if they do not understand the research as well as the research team. Science does not have to stop until the public are all scientists. Scientists do, however, need to protect non-scientist interests, even when it feels like doing so gets in the way of progress. The discussion of the ethical challenges is not meant to detract that we, as a society, need this kind of research if we hope to continue improving overall health. The brain is boundlessly complex, and we do not understand it well enough to adequately treat those who need it. In short, our deep ignorance of the brain’s inner workings requires deep, and sometimes invasive, research.


________________


 Nathan Ahlgrim is a fifth year Ph.D. candidate in the Neuroscience
Program at Emory. In his research, he studies how different brain
regions interact to make certain memories stronger than others. He strengthens his own brain power by hiking through the north
Georgia mountains and reading highly technical science...fiction.


References


Appelbaum PS, Roth LH, Lidz C (1982) The therapeutic misconception: Informed consent in psychiatric research. International journal of law and psychiatry 5:319-329.


Chiong W, Leonard MK, Chang EF (2018) Neurosurgical patients as human research subjects: Ethical considerations in intracranial electrophysiology research. Neurosurgery 83:29-37.


Corrigan PW (2002) Empowerment and serious mental illness: Treatment partnerships and community opportunities. Psychiatric Quarterly 73:217-228.


Corrigan PW, Watson AC, Barr L (2006) The self–stigma of mental illness: Implications for self–esteem and self–efficacy. Journal of Social and Clinical Psychology 25:875-884.


Dunn LB, Holtzheimer PE, Hoop JG, Mayberg HS, Roberts LW, Appelbaum PS (2011) Ethical issues in deep brain stimulation research for treatment-resistant depression: Focus on risk and consent. AJOB Neuroscience 2:29-36.


Faden RR, Beauchamp TL (1986) A history and theory of informed consent: Oxford University Press.


Fang FC, Casadevall A (2010) Lost in translation—basic science in the era of translational research. Infection and Immunity 78:563-566.


Inman CS, Manns JR, Bijanki KR, Bass DI, Hamann S, Drane DL, Fasano RE, Kovach CK, Gross RE, Willie JT (2017) Direct electrical stimulation of the amygdala enhances declarative memory in humans. Proceedings of the National Academy of Sciences.


Labuzetta JN, Burnstein R, Pickard J (2011) Ethical issues in consenting vulnerable patients for neuroscience research. Journal of Psychopharmacology 25:205-210.


Miller FG, Wertheimer A (2011) The fair transaction model of informed consent: An alternative to autonomous authorization. Kennedy Institute of Ethics Journal 21:201-218.


Müller S, Christen M (2011) Deep brain stimulation in parkinsonian patients—ethical evaluation of cognitive, affective, and behavioral sequelae. AJOB Neuroscience 2:3-13.


Palmer BW, Savla GN, Roesch SC, Jeste DV (2013) Changes in capacity to consent over time in patients involved in psychiatric research. The British Journal of Psychiatry 202:454-458.


Resch A, Berk J, Akers L (2014) Recognizing and conducting opportunistic experiments in education: A guide for policymakers and researchers In. Washington, D.C.: U.S. Department of Education.


Swift T (2011) Desperation may affect autonomy but not informed consent. AJOB Neuroscience 2:45-46.


Want to cite this post?


Ahlgrim, N. (2018). How to be Opportunistic, Not Manipulative. The Neuroethics Blog. Retrieved on , from http://www.theneuroethicsblog.com/2018/10/how-to-be-opportunistic-not-manipulative.html


Tuesday, July 24, 2018

Exploring the Risks of Digital Health Research: Towards a Pragmatic Framework


By Dr. John Torous


Image courtesy of Flickr user Integrated Change

We often hear much about the potential of digital health to revolutionize medicine and transform care – but less about the risks and harms associated with the same technology-based monitoring and care. “It’s a smartphone app … how much harm can it really cause?” is a common thought today, but also the starting point for a deeper conversation. That conversation is increasingly happening at Institutional Review Boards (IRBs) as they are faced with an expanding number of research protocols feature digital- and smartphone-based technologies.


In our article, ‘Assessment of Risk Associated with Digital and Smartphone Health Research: a New Challenge for IRBs” published in the Journal of Technology and Behavioral Science [1], we explore the evolving ethical challenges in evaluating digital health risk, and here expand on them. While risk and harm in our 21st century digital era are themselves evolving topics that change with both technology and societal norms, how do we quantify them to help IRBs in making safe and ethical decisions regarding clinical research?


A first step is to consider what is the baseline risk of any online or connected technology. Take for example privacy. In countries like the United States, internet service providers can now legally collect and sell users’ web browsing history without consent [2]. Popular websites such as Facebook may at times track users even when logged out or sometimes even without them ever having signed up [3]. The uses of this digital data can range the gamut from targeted advertising to police subpoenas of Fitbit and smartphone data for criminal prosecution [4]. With so much personal data already being collected in everyday life as the price of admission for use of today’s online services, what qualifies as high or low risk digital data collection in a clinical study or even everyday life? In Europe, this question has led to the new General Data Protection Regulation (GDPR) that took effect on May 25th 2018 [4] and set new strict and enforceable standards for online privacy, the right to be forgotten, data portability, data access, and breach notifications. Whether other countries will follow and pass legislation similar to the GDPR remains to be seen, but until then the question of assessing risks around privacy remains challenging for IRBs, researchers, and the public.


Image courtesy of Pixabay

While privacy is the chief risk considered today with online-, sensor-, and smartphone-based research, as these tools develop so does their potential to create new risks. Three other types of risks that are important to consider are physical, psychological, and financial. In the published literature, there are surprisingly few cases of physical harm resulting from smartphone-based research studies which may in part reflect that most studies today focus on monitoring or lowering risk lifestyle interventions. There is also a paucity of data on psychological harms from smartphone-based studies or how people may react to being closely monitored, for example via GPS on their smartphone, etc. Likewise, there has been little reported on financial risks associated with inadvertent disclosure of digital data collected by sensors and smartphones. This is not to say these risks are minimal, but rather that as a field we need to better study and quantify these risks and their magnitude of harm. Without good data, it is challenging for IRBs to make informed decisions about studies - and equally challenging for research participants to make informed decisions about joining that study.


Further considerations that are more unique to digital health studies include assessing technology literacy and bystander risk. While words like ‘GPS,’ ‘anonymized data,’ and ‘hashing’ are frequently used in informed consent documents for smartphone studies, it is important to ensure that those signing informed consent actually understand what these words mean. Do you know the difference between de-identified and anonymized data? There is some research suggesting that those with lower health literacy may also be vulnerable to assuming health technologies like smartphone apps, etc. are safer and more secure than they actually are [6]. This raises the issue of a new digital divide not based on access to technology, but rather on understanding risks and equitable utilization. Yet another risk to consider that does not often occur in classical clinical research but more frequently with digital technology studies is bystander risk. Voice recordings may capture other voices in the nearby vicinity, Bluetooth monitoring will record information about nearby smartphones, and cameras may capture an entire scene with others in it.


Image courtesy of Wikimedia Commons

Putting it all together, the model below seeks to guide IRBs through considering the different types of risk as well as ways to mitigate them. While this model is not designed to be comprehensive or thorough for every type of digital health study for every type of clinical population, hopefully the basic themes and examples provided may help guide informed decision making.


Recognizing risks in digital health studies is not an exercise in hindering research, but rather the pathway to mitigate risk and help ensure safer and better studies. For example, the largest risk factor of privacy is actually often the easiest to mitigate with appropriate encryption and security protocols. Ensuring that informed consent language is appropriate for those who are less technology-literate can help them better understand the study and be more interested in meaningfully participating. Communities like the Connected and Open Research Ethics (CORE) offer free and easy access to support and online forums for researchers, IRBs, and anyone to ask questions and receive answers on digital health ethics. The Neuroethics Blog you are reading right now also offers a wealth of relevant posts to help guide ethical decision making in this digital era. But perhaps the best resources of all remains an open mind willing to explore not only the benefits of digital technology, but also ponder the risks in order to bring both sides together for more informed decision making.


_______________


John Torous MD is director of the digital psychiatry division at Beth Israel Deaconess Medical Center at Harvard Medical School. As a board-certified psychiatrist with a background in computer sciences and clinical informatics, his research on smartphone apps and sensors for predicating relapse in serious mental illnesses like schizophrenia bridges engineering and clinical care. In 2017, Dr. Torous was awarded the Carol Davis Ethics Award by the American Psychiatric Association, an annual award for ethics and mental health work. 


References

1. Torous J, Roberts LW. Assessment of Risk Associated with Digital and Smartphone Health Research: a New Challenge for Institutional Review Boards. Journal of Technology in Behavioral Science. 2018:1-5.


2. FCC releases proposed rules to protect broadband consumer privacy (2016). Federal Communications Commission. https://www.fcc.gov/document/fcc-releases-proposed-rules-protect-broadband-consumer-privacy. 


3. https://www.buzzfeed.com/alexkantrowitz/heres-how-facebook-tracks-you-when-youre-not-on-facebook?utm_term=.loGrdzO1g#.eiED5XZR2


4. https://www.washingtonpost.com/local/public-safety/commit-a-crime-your-fitbit-key-fob-or-pacemaker-could-snitch-on-you/2017/10/09/f35a4f30-8f50-11e7-8df5-c2e5cf46c1e2_story.html?noredirect=on&utm_term=.a4acd2fba4ea


5. https://www.eugdpr.org/


6. Mackert M, Mabry-Flynn A, Champlin S, Donovan EE, Pounders K. Health literacy and health information technology adoption: the potential for a new digital divide. Journal of medical Internet research. 2016 Oct;18(10).


Want to cite this post?


Torous, J. (2018). Exploring the Risks of Digital Health Research: Towards a Pragmatic Framework . The Neuroethics Blog. Retrieved on , from http://www.theneuroethicsblog.com/2018/07/exploring-risks-of-digital-health.html

Tuesday, February 14, 2017

Predicting Psychosis: Exploring Pre-Clinical Signs for Mental Illness


By Sunidhi Ramesh


This post is based on the January edition of the “Neuroethics and Neuroscience in the News” series in which Dr. Elaine Walker from Emory University discussed the ethics of assessing risk and treating brain diseases before they can be diagnosed.


This self-portrait is often used to depict the distorted

reality that many schizophrenia patients face.

(Image courtesy of Wikimedia Commons.)

“This calculator,” a 2016 headline states, “can predict your risk of developing psychotic disorders.”


Psychotic disorders, including schizophrenia and bipolar disorder with psychotic features, are characterized by noticeable deficits in “normal” behavior accompanied by hallucinations, delusions, paranoia, an early onset (the average age of onset is in the late teens or early twenties), and a derailed life course.


Because of its early age at onset, the DALY (disability adjusted life years) value for psychosis is significantly greater than that of other illnesses (1). It’s no surprise, then, that researchers are asking questions. Are there measures that can be taken to keep at-risk populations from enduring a life-hindering disability?


Fifteen years ago, the answer would be no. Today, it (just might be) yes. 


How? Researchers have recently identified patterns in pre-clinical psychotic symptoms— patterns that many psychotic patients exhibit long before they are formally diagnosed with a disorder.


In schizophrenia and other psychotic disorders that “interfere with a person’s ability to think clearly, manage emotions, make decisions and relate to others,” this pre-clinical period is called the prodromal period. During this time, patients often experience gradual disruptions in behavioral functioning (like being suspended from school or losing friends) that are accompanied by subclinical or reduced psychotic symptoms (like hallucinations and delusions).


A cloth embroidered by a schizophrenia patient.

(Image courtesy of Wikimedia Commons.)

Countries such as Australia have found ways to make the diagnosis for these pre-clinical symptoms even easier to detect through modern technology and the Internet. Websites are now in place where young people can respond to questions about psychotic symptoms that they may be experiencing and determine for themselves if they should seek mental health care. While it is important to consider the ethical grounds of allowing or encouraging potential patients to “self-diagnose” risk for psychosis (with such ethical concerns including denial of symptomology, missed diagnosis, under/overdiagnosis, and misdiagnosis), most of these tests are thought to be preliminary efforts to encourage patients to pursue mental health treatment in the first place.


In 2008, eight independent research institutions (Emory University, Harvard University, University of California Los Angeles (UCLA), University of California San Diego (UCSD), University of North Carolina Chapel Hill, University of Toronto, Yale University, and Zucker Hillside Hospital) combined efforts to research the onset and symptomology of psychotic disorders. They titled their project the North American Prodrome Longitudinal Study, or NAPLS for short.


Historically, accounts of patients with schizophrenia-like conditions began to appear in records around the 19th century (2). The word “schizophrenia” itself translates directly to “splitting of the mind,” hinting at the divisive nature of the illness and its symptoms (3).


Demographically, the disorder afflicts about 1% of the worldwide population (4). 


One patient writes:


 “Schizophrenia isn’t about what you think it is (for example, I haven’t scrawled a bunch of complex mathematical equations on a window lately). It’s loud. It is so, so loud—the voices in your head and the voices outside your head and the typing of keys and the vibrations of phones and the TV and the brewing of coffee and the footsteps behind you. Does he need to follow so closely? I’m sorry, what did you just say? I was too busy listening to the voice telling me I’m a loser.  


And my loud world can only be quieted with meds that can take two months to end up in my medicine cabinet because securing an appointment with my psychiatrist is such an ordeal. And those meds often end up causing acne or depression or diarrhea, or leave me barely able to function—let alone work efficiently. (Sometimes I need to sleep 12 hours and take two daytime naps just to stay alive.) (5)”


During her talk for the January edition of the Neuroscience and Neuroethics in the News series, Dr. Walker emphasized that NAPLS specifically has “generated an interest in the prodromal [pre-clinical] phase of illness, the stage just prior to florid psychosis.” It is in this phase, long before patients meet the DSM-5 criteria for psychotic disorders, that these individuals show a decline in normal function and the gradual onset of psychotic (among other) symptoms. Some studies suggest that the longer the period of the prodromal phase, the worse the prognosis will be for the individual down the line (6). Although the reason for this pattern is still unknown, it is apparent that early, pre-emptive interventions may be able to reduce future behavioral maladaptations and psychotic symptoms.


Schizophrenia is often characterized by strong, auditory

hallucinations-- colloquially called "hearing voices."

(Image courtesy of Deviant Art.)

How is this prodromal phase identified? Researchers at Yale University have developed a structured diagnostic interview, the Structured Interview for Prodromal Syndromes (SIPS). This assessment “evaluate[s] and monitor[s] prodromal symptoms for at-risk and comparison subjects” by quantifying characteristically attenuated psychotic symptoms, such as unusual thought content, suspiciousness, perceptual abnormalities, and disorganized communication (7). SIPS also identifies a “clinical high-risk group”— individuals in this group “have high rates of conversion to psychosis (ranging from 15-35% in most studies) over about two years.” It is under this presumption that the aforementioned psychosis calculators were developed.


From here, patients who are identified as “high risk” are admitted into programs (such as the Prodrome Assessment Research and Treatment (PART) program in San Francisco) and monitored over time. They are given resources and therapy that are aimed at helping them cope with their symptoms while better understanding what it means to have the experiences that they do.


Dr. Walker also highlighted that the standard of care in these cases does not involve antipsychotic medication. In most programs for individuals showing signs of the prodrome for psychosis, antipsychotics are only recommended when an individual meets the criteria for a psychotic disorder, and prodromal patients, by definition, do not. Basic interventions and therapy efforts (including simple monitoring, family support groups, and interventions aimed at enhancing coping mechanisms), however, have been shown to have a positive effect on high-risk patients impacted by these prodromal symptoms (8). Without a diagnosis, most high-risk patients lack a framework to refer to their illness and struggle to understand what is happening to their lives.


Nevertheless, while detecting psychosis early provides great room for intervention, mediation, and monitoring, it is important to understand that there exist potential dangers to labeling an individual as clinically “high risk” in the first place.


Schizophrenia translates to "splitting of the mind" in Greek.

(Image courtesy of Flickr.)

Among these concerns are the consequences of false negatives and false positives as well as the potential for future discrimination that these patients may face from insurance companies or from the broader world. As with all pre-clinical syndromes, the ethical implications of such errors occurring during assessment must be considered in conjunction with the research being conducted in order to ensure that both current and future patients receive the best treatment (9).


False negatives, in the context of the prodromal phase of schizophrenia, would be patients who are not identified as “high risk” through the SIPS assessment but are then diagnosed with the disorder at a later age. This type of error may lead to delays in the provision of treatment for the patient after the clinical onset of psychosis (“It can’t be any mental disorder, so maybe he is just acting up and being a typical teenager.”) or may cause varying levels of frustration with not being able to understand and label symptoms themselves or even the condition as a whole (“She doesn’t have schizophrenia, so why is she acting this way? Why is he losing his friends and wanting to drop out of school? What are these voices she is hearing?”). With the lack of a definitive prodromal assessment, patients and families may automatically assume that schizophrenia is out of the question and may subsequently “miss opportunities to intervene” (9).


False positives then, in the context of the prodromal phase of schizophrenia, would be patients who are identified as “high risk” through the SIPS assessment but are then not diagnosed with the disorder at a later age. These cases can lead to families investing in “unnecessary expensive interventions, surveillance, and treatments as well as lead to changes in the life trajectories of the patient, caregivers, and entire family” (in the case that the family makes large lifestyle changes to accommodate the patient’s newly identified condition) (9). And, if prolonged, false positive results may also give rise to larger psychosocial consequences (10).


Ultimately, to circumvent these errors, physicians and researchers are trained in appropriately debriefing patients and their families about the full range of possibilities for the subsequent developmental trajectory of individuals who meet criteria for “clinical high risk.”


(Image courtesy of Flickr.)

If such information were to become part of the individual’s medical record, some ethicists also raise the concern that patients from these pre-clinical studies may be at risk for employment and insurance discrimination, as current laws in patient protection are vague regarding the difference between “diagnosis” and pre-clinical “risk-assessments” (11). As these trials continue to increase in abundance, then, specific policy must be put into place by lawmakers (with consultation from researchers) to reduce current ambiguity and protect the rights of all patients involved.


Ultimately, as medicine moves towards early detection and disease modification, we will only see more forms of these early-detection technologies emerge not only in the realm of mental health but also for other illness in general.


During this progression, it will be critical for these ethical considerations to be explored continuously, in union with further research.


(This event was a sneak peek for an upcoming neuroscience graduate student-led symposium slated for April 28, 2017 on "The use of preclinical biomarkers for brain diseases: A Neuroethical Dilemma." This symposium will highlight preclinical detection technologies across the human lifespan, from infants to adolescents to the elderly.)


References 


1) Jones, P. B. "Adult mental health disorders and their age at onset." The British Journal of Psychiatry 202.s54 (2013): s5-s10.


2) Heinrichs RW (2003). "Historical origins of schizophrenia: two early madmen and their illness". Journal of the History of the Behavioral Sciences. 39 (4): 349–63.


3) Park, Sohee, and Katharine N. Thakkar. "' Splitting of the Mind' Revisited: Recent Neuroimaging Evidence for Functional Dysconnection in Schizophrenia and Its Relation to Symptoms." (2010): 366-368.


4) Gochman, Peter, Rachel Miller, and Judith L. Rapoport. "Childhood-onset schizophrenia: the challenge of diagnosis." Current psychiatry reports 13.5 (2011): 321.


5) "What It's Really Like To Have One Of The World's Most Stigmatized Mental Health Issues." GOOD Magazine. N.p., 04 Feb. 2017. Web. 08 Feb. 2017.


6) Yung, Alison R., and Patrick D. McGorry. "The prodromal phase of first-episode psychosis: past and current conceptualizations." Schizophrenia bulletin 22.2 (1996): 353-370.


7) Addington, Jean, et al. "North American Prodrome Longitudinal Study: a collaborative multisite approach to prodromal schizophrenia research." Schizophrenia bulletin 33.3 (2007): 665-672.


8) Kaur, Tejal, and Kristin S. Cadenhead. "Treatment implications of the schizophrenia prodrome." Behavioral Neurobiology of Schizophrenia and Its Treatment. Springer Berlin Heidelberg, 2010. 97-121.


9) Sarrett, Jennifer C., and Karen S. Rommelfanger. "Commentary: Attention to Eyes Is Present but in Decline in 2–6-Month-Old Infants Later Diagnosed with Autism." Frontiers in public health 3 (2015).


10) Brodersen, John, and Volkert Dirk Siersma. "Long-term psychosocial consequences of false-positive screening mammography." The Annals of Family Medicine 11.2 (2013): 106-115.


11) Arias, Jalayne J., and Jason Karlawish. "Confidentiality in preclinical Alzheimer disease studies When research and medical records meet." Neurology 82.8 (2014): 725-729.


Want to cite this post?


Ramesh, Sunidhi. (2017). "Predicting Psychosis: Exploring Pre-Clinical Signs for Mental Illness." The Neuroethics Blog. Retrieved on , from http://www.theneuroethicsblog.com/2017/02/predicting-psychosis-exploring-pre.html


Tuesday, July 15, 2014

Intellectual Property from Clinical Research on Neuropsychiatric Disorders: What Constitutes Informed Consent?

By Elaine F. Walker, Ph.D. & Arthur T. Ryan, M.A.


Elaine Walker is a Professor of Psychology and Neuroscience in the Department of Psychology at Emory University and is the Director of the Development and Mental Health Research Program, which is supported by the National Institute of Mental Health. Her research is focused on child and adolescent development and the brain changes that are associated with adolescence. She is also a member of the AJOB Neuroscience editorial board.


The pace of advances in biomedical research has accelerated in conjunction with new technologies for studying cellular processes. While this progress holds promise for relieving human suffering from a range of illnesses, it also poses significant and thorny questions about the ownership of new knowledge. In June of 2013, the Supreme Court issued a unanimous ruling on the Association for Molecular Pathology v Myriad Genetics, Inc.; all justices agreed that naturally occurring DNA sequences cannot be patented1. This ruling was precipitated by a patent owned by Myriad genetics on the DNA sequences for the human BRCA1 and BRCA2 genes, which are associated with human variation in susceptibility to cancer. The ruling concluded that genes are products of nature and, therefore, cannot be claimed as the intellectual property (IP) of any individual or commercial entity. Within hours after this ruling, other companies announced that they would offer genetic testing for BRCA1 and BRCA2 at a significantly lower cost than Myriad had been charging for years.


While the Supreme Court's ruling on the patentability of naturally occurring human genetic sequences had broad and immediate implications, it represents only the tip of the iceberg with respect to the contentious issues that will confront intellectual property (IP) rights for future biomedical advances. We can anticipate more ethical and legal debates regarding commercialization in the fields of proteomics (the study of protein structure and function), epigenetics (changes in gene expression mediated by RNA, as opposed to changes in the DNA code), stem cells, and the study of the human connectome (the map of neural connections in the brain). The implications of the pursuit of patents in these areas will extend to all fields of medicine, but they present some particularly complex problems with regard to the brain disorders that are the province of neurology and psychiatry.


By way of background, most consent forms approved by institutional review boards (IRBs) do not explicitly inform prospective participants that IP may be generated using the biospecimens they provide during their participation. Some have argued that researchers are ethically obligated to inform participants that the investigator may benefit financially from the research, whereas the participant will not2. On the other hand, it has been argued that individuals who are capable of providing informed consent would be expected to be aware that patents might be obtained on marketable biomedical products that result from scientific advances3.


Can the same assumptions be made for all prospective participants? Clinical research aimed at elucidating the causes and effective treatments for neuropsychiatric disorders are dependent on the participation of volunteers who are either at risk for, or diagnosed with, such a disorder. This includes studies of individuals at risk for psychotic and mood disorders, and dementia and other neurodegenerative illnesses. As a result, these research volunteers may be suffering from symptoms that impair their cognitive capacities. Such impairments have the potential to diminish their ability to comprehend the information provided during the consenting process, as well as their comprehension of the broader implications of their property rights to their biospecimens and the knowledge that might be generated with them4. Nonetheless, informed consent procedures are used with these clinical research populations, albeit with extra consideration given to assure their understanding of the procedures. Ruling out informed consent by individuals who may be suffering from, or at risk for, a brain disorder would severely compromise scientific progress on these illnesses. At the same time, the ethical complexities of patents on the IP generated by such research cannot be ignored.


Concerns about risk status are a motivator for many participants in clinical research. Most IRBs require that consent forms include a ‘disclaimer’ statement concerning the likely absence of direct benefit to the participant. Yet, it is not clear that most prospective participants, especially those at risk for neuropsychiatric disorders, are aware that they may not have access to any advances in risk prediction that accrue from the research in which they participate. Thus, if a diagnostic test that enhances risk prediction and/or informs effective treatment results from the research, participants may assume that their access to it is assured. Yet this may not be the case if the ‘discovery’ becomes IP and the investigator applies for a patent.


Several scenarios may ensue and these are unlikely to be anticipated by most participants. For example, the pursuit of a patent may delay the public disclosure of the research findings, and in the interim the individual may succumb to an illness that might have been prevented if the discovery had been more promptly revealed. Further, the cost of the patented diagnostic test may be prohibitive for the individual, despite the fact that the participant contributed biospecimens that were used for the test's development. While such concerns are not unique to neuropsychiatric research, the ethical concerns are amplified in the case of individuals with cognitive impairments.


If participants were informed, as is the case in some European nations, that the researchers may benefit financially from discoveries made using their biospecimens, would that affect their willingness to participate? Although we are not aware of any research directly addressing this question, the results of studies of the general population indicate that many would be disinclined to consent to research participation if they were so informed 3,5.


It is clear that research advances in biomedical risk assessment, combined with trends toward commercialization, raise serious questions that are likely to become even more salient. Perhaps the most important question we must address is what information should be conveyed while obtaining the informed consent of prospective clinical research participants who provide biospecimens that might be used for commercial purposes. The ethical issues in this arena are especially noteworthy when the study population is characterized by limited cognitive capacity and when individual participants may be motivated by the desire for illness prevention or treatment access.


References


1. Ass’n for Molecular Pathology v. Myriad. Ct 133, 2107 (2013).


2. Godard, B., Schmidtke, J., Cassiman, J.-J. & Aymé, S. Data storage and DNA banking for biomedical research: informed consent, confidentiality, quality issues, ownership, return of benefits. A professional perspective. Eur. J. Hum. Genet. 11, S88–S122 (2003).


3. Steinsbekk, K. S., Ursin, L. Ø., Skolbekken, J.-A. & Solberg, B. We’re not in it for the money—lay people’s moral intuitions on commercial use of ‘their’biobank. Med. Health Care Philos. 16, 151–162 (2013).


4. Caplan, A. L. & Arp, R. Contemporary Debates in Bioethics. (John Wiley & Sons, 2013).


5. Sterckx, S., Cockbain, J., Howard, H., Huys, I. & Borry, P. ‘Trust is not something you can reclaim easily’: patenting in the field of direct-to-consumer genetic testing. Genet. Med. 15, 382–387 (2013).


Other Relevant Articles 


Andrews, L. B., & Paradise, J. (2005). Gene patents: the need for bioethics scrutiny and legal change. Yale J. Health Pol'y L. & Ethics, 5, 403.


DuBois, J. M., Beskow, L., Campbell, J., Dugosh, K., Festinger, D., Hartz, S., ... & Lidz, C. (2012). Restoring balance: a consensus statement on the protection of vulnerable research participants. American journal of public health, 102(12), 2220-2225.


Kim, S. Y., Caine, E. D., Currier, G. W., Leibovici, A., & Ryan, J. M. (2001). Assessing the competence of persons with Alzheimer’s disease in providing informed consent for participation in research. American Journal of Psychiatry, 158(5), 712-717.


Klein, R. D. (2013). AMP v Myriad: The Supreme Court Gives a Win to Personalized Medicine. The Journal of Molecular Diagnostics, 15(6), 731-732.


Rojahn, Susan Y. Cheaper Genetic Tests for Breast Cancer Risks in 2014? MIT Technology Review, December 31, 2013.


Want to cite this post?


Walker, E., Ryan, A. (2014). Intellectual Property from Clinical Research on Neuropsychiatric Disorders: What Constitutes Informed Consent? The Neuroethics Blog. Retrieved on , from http://www.theneuroethicsblog.com/2014/07/intellectual-property-from-clinical.html